Buccal Massage vs. TMJ Manual Therapy: What Is the Difference? – The Canadian Health Academy blog graphic in Maple Red, black and gray

Buccal Massage vs. TMJ Dysfunction Manual Therapy: What Is the Difference?

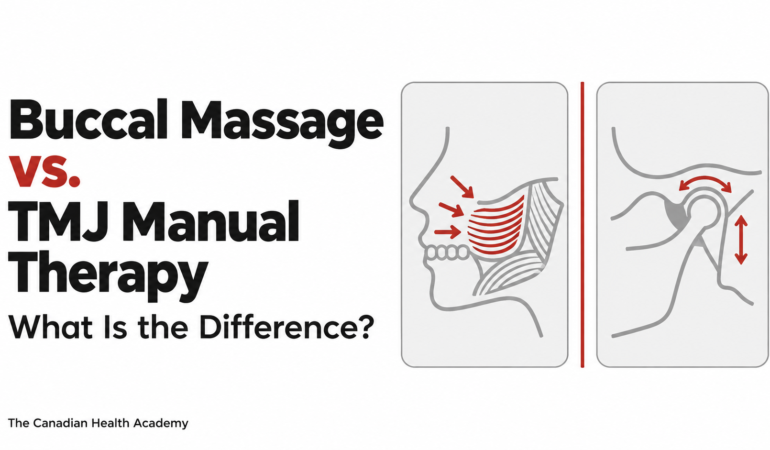
“Buccal massage” has gone from a niche technique to a social media trend, and clients now arrive asking for it by name, sometimes for a sore jaw as much as for a facial. At the same time, manual therapy for temporomandibular joint (TMJ) dysfunction is a long-established part of rehabilitation and manual therapy practice. Both can involve working inside the mouth, which is why the two are often confused. For massage therapists, physiotherapists, and other healthcare practitioners, the distinction matters for assessment, consent, evidence and scope of practice. This article explains how they differ, what the research says, and what to consider before adding either to your services.

What Is Buccal Massage?

Buccal massage, also called intraoral massage, takes its name from the Latin word for cheek. In a typical session, the practitioner places gloved fingers inside the mouth, in the space between the teeth and the inside of the cheek, and works with a thumb on the outside to stretch and massage the cheek tissues [1]. It is most often offered as a facial or facial-wellness service, with claims about contouring, puffiness and facial tension.

The evidence base is thin. A university health-science commentary noted that there are no rigorous controlled studies showing that buccal massage produces a lasting change in facial contour, and described claims of a lasting lift as anecdotal [1]. The same source acknowledged that facial massage may give some relief to people with jaw clenching or bruxism when it relaxes tense muscle [1].

What Is Manual Therapy for TMJ Dysfunction?

Temporomandibular disorders (TMD) are considered the main musculoskeletal cause of orofacial pain. They are a group of conditions, and can involve the joint itself, a displaced disc, hypermobility or the muscles of mastication [2]. Manual therapy for TMD is a clinical intervention aimed at a defined problem, such as jaw pain, restricted mouth opening, clicking or muscle tension, identified through assessment.

Techniques vary by practitioner and profession. Trial protocols describe, for example, intraoral release of the masseter, temporalis, and lateral and medial pterygoid muscles using inhibition, along with joint techniques that distract and articulate the mandible [6]. Other approaches treat the cervical region as well, because neck and jaw function are linked [4]. Many programs combine hands-on work with home exercise [2].

Key Differences at a Glance

Feature Buccal massage Manual therapy for TMJ dysfunction
Main purpose Facial wellness, relaxation, appearance-related goals; sometimes jaw tension Reducing pain and improving jaw function in a client with TMD symptoms
How it starts Often a service request Health history, symptom review and a jaw and neck assessment
Techniques Intraoral stretching and kneading of the cheek with outside counter-pressure [1] Intraoral and extraoral soft tissue work, joint mobilization, often cervical work and exercise [2][4][6]
Structures involved Cheek tissues and buccinator region; deeper muscles are sometimes described Masticatory muscles, TMJ, and often the neck
Evidence No rigorous controlled studies of buccal massage itself [1] Randomized trials and systematic reviews, with mixed quality [2][3][4]
Outcomes measured Rarely measured Pain, maximum mouth opening, function [2][3]
Practitioner skill needed Intraoral technique, infection control, consent All of that, plus orofacial assessment, clinical reasoning and referral judgment

Where the Two Overlap

The overlap is real. Both can involve gloved work inside the mouth, and both can touch muscles such as the masseter. A relaxation-oriented buccal massage may ease a clenched jaw, and a TMD treatment may include techniques that look very similar to buccal work. What differs is the clinical framework. In TMD care, the intraoral technique is one tool selected because of an assessment finding, tracked against outcomes such as pain and mouth opening, and paired with advice and exercise. In a standard buccal facial, the technique is the service.

That distinction affects how you describe your work to clients. A practitioner who offers buccal massage for general facial tension should avoid implying that it treats a TMJ condition. A client with persistent jaw pain, locking or clicking deserves an assessment, and possibly a referral, not only a facial.

What Does the Research Say About TMJ Manual Therapy?

Medium-term effects. A systematic review and meta-analysis of six randomized trials, each with at least three months of follow-up, found significant improvement in pain and mouth opening compared with baseline after manual therapy. The effect appeared to fade over time, but combining manual therapy with therapeutic exercise helped maintain the benefit in the longer term [2].

Short-term effects across professions. A 2026 systematic review of 18 randomized trials on manual therapy for TMD, including treatment by different healthcare professionals, concluded that manual therapy may be associated with short-term improvements. The authors framed the question of which techniques and professional approaches work best as still unclear [3].

The cervical spine. A meta-analysis found that cervical manual therapy reduced pain intensity more than placebo manual therapy or minimal intervention in people with TMD, with moderate evidence. Combined cervico-craniomandibular treatment gave larger short-term reductions in pain and improvements in pain-free mouth opening than cervical treatment alone, but the evidence was low [4].

Intraoral massage specifically. A small randomized, placebo-controlled trial of 40 women with muscle-related TMD compared intraoral, extraoral and combined massage. The authors reported that combined and intraoral massage improved signs and symptoms [5]. This is a small, early study reported in a conference abstract, so it should be read as preliminary.

Why the evidence is limited

Across the TMD literature, trials are small, techniques differ, and the quality is variable [2][3]. Neither strong claims nor outright dismissal are supported. For buccal massage as a stand-alone cosmetic treatment, the situation is more basic: there is little research to review at all [1].

Safety, Consent and Scope in Ontario

  • Infection control. Because the practitioner’s fingers are inside the client’s mouth, excellent hand hygiene and infection prevention and control measures, including gloves, are essential [1]. Safety data for buccal massage itself are lacking [1].
  • Informed consent. The College of Massage Therapists of Ontario’s Standards of Practice, in effect since January 1, 2022, cover informed consent, consent for treatment of sensitive areas, an evidence-informed approach, and staying within the massage therapy scope of practice [7]. Intraoral work calls for especially clear explanation and consent.
  • Know when to refer. Good practice is to defer or refer when a client presents with recent facial or jaw trauma, a jaw that is locked or cannot open, signs of infection or dental pain, unexplained swelling, or neurological symptoms. Apply your own profession’s guidance here.
  • Check your scope and coverage. Confirm with your regulatory college and professional liability insurer that intraoral techniques are within your scope and covered before offering them.

Which Should You Offer?

The answer depends on your profession and your clients:

  • If your clients mainly want facial relaxation: buccal massage may fit a wellness-oriented service, as long as you are transparent about the limited evidence, avoid contouring or treatment claims, and meet infection-control and consent standards.
  • If clients present with jaw pain, clicking or limited opening: a TMD-focused approach built on assessment, outcome tracking, cervical screening and home exercise is better supported by research [2][4].
  • If you want to do both: keep the two services clearly separate in how you book, document and describe them.

Building Your Skills with Healthcare Continuing Education in Ontario

Jaw and facial work builds on strong head, neck and soft tissue skills. If you are looking for healthcare continuing education in Ontario to support this kind of practice, The Canadian Health Academy offers hands-on courses in Mississauga that complement it:

As a health academy in Ontario, we provide healthcare training and healthcare therapy training for practitioners who want to expand their skills. Browse every program on our courses page, see our Continuing Education Brampton page for healthcare continuing education in Brampton, or visit the Registration page. Looking for healthcare certification courses and continuing education for healthcare professionals in Ontario? Contact us and we will help you find the right fit.

Frequently Asked Questions

Is buccal massage the same as TMJ massage?

No. Both can involve intraoral work, but buccal massage is usually offered as a facial service, while TMJ manual therapy is a treatment for a client with jaw symptoms, based on assessment and outcome tracking [1][2].

Does buccal massage help TMJ pain?

Facial massage may relieve some tension in people who clench or grind, but there is no rigorous research on buccal massage itself for TMJ conditions [1]. Manual therapy aimed at TMD has a larger research base, though of mixed quality [2][3].

Is intraoral massage safe?

Safety data for buccal massage are lacking, and infection control is essential because fingers are inside the mouth [1]. Screening, informed consent and appropriate referral are key.

Can Registered Massage Therapists in Ontario do intraoral work?

This depends on your scope of practice, training and your college’s standards. Confirm with the College of Massage Therapists of Ontario and your insurer before offering it [7].

Conclusion

Buccal massage and manual therapy for TMJ dysfunction share a technique but not a purpose. Buccal massage is typically a facial wellness service with little supporting research. TMJ manual therapy is a clinical intervention built on assessment, outcome measures, and, ideally, exercise, with a research base that is promising but mixed. For practitioners, the value lies in knowing which you are offering, describing it honestly, screening carefully and staying within scope.

This article is for educational purposes for healthcare and wellness professionals and does not replace individual clinical assessment. Check your regulatory college and insurer regarding scope of practice.

References

  1. University of Technology Sydney. Could buccal massage make you look older, not younger? UTS Newsroom, 16 February 2023. uts.edu.au
  2. Herrera-Valencia A, Ruiz-Muñoz M, Martín-Martín J, Cuesta-Vargas A, González-Sánchez M. Efficacy of manual therapy in temporomandibular joint disorders and its medium- and long-term effects on pain and maximum mouth opening: a systematic review and meta-analysis. Journal of Clinical Medicine. 2020;9(11):3404. doi:10.3390/jcm9113404
  3. Efficacy of manual therapy by different healthcare professionals on pain and function in temporomandibular disorders: a systematic review of randomized controlled trials. 2026. doi:10.1080/10669817.2026.2629282
  4. Effect of manual therapy and therapeutic exercise applied to the cervical region on pain and pressure pain sensitivity in patients with temporomandibular disorders: a systematic review and meta-analysis. Pain Medicine. 2020;21(10):2373-2384. doi:10.1093/pm/pnaa021
  5. Gama MCS, Rizatti-Barbosa CM, Alves MC, Bérzin F. Techniques of massage therapy in myogenous temporomandibular disorder: a randomized placebo-controlled trial. Conference poster, International Society of Biomechanics, 2013. isbweb.org
  6. The effect of intra-oral osteopathic technique on pain, maximum mouth opening, and disability in patients with chronic temporomandibular joint disorder. Australian New Zealand Clinical Trials Registry. anzctr.org.au
  7. Registered Massage Therapists’ Association of Ontario. New CMTO Standards of Practice (effective January 1, 2022). rmtao.com

Read More
Cupping Therapy: What the Evidence Says – The Canadian Health Academy blog graphic in Maple Red, black and gray

Cupping Therapy for Practitioners: What the Evidence Says and How to Get Trained in Ontario

Round, circular marks on a client’s back have become a familiar sight in clinics, gyms and on social media, and more clients now ask their therapists about cupping by name. For massage therapists, physiotherapists, kinesiologists and other healthcare practitioners, the practical questions are the same as for any adjunct technique: what does the research actually show, how safe is it, and what training should you have before you use it? This article answers those questions from the published literature, and then looks at what to consider when choosing a cupping therapy course in Ontario.

What Is Cupping Therapy?

Cupping applies cups to the skin to create negative pressure (suction) over a treatment area. It is an ancient practice, and today it is used mainly for musculoskeletal pain and soft tissue complaints [5]. Clinicians describe several types, including dry cupping, wet cupping, and cupping massage, where cups are moved over lubricated skin [7]. A typical cupping set contains a range of cup sizes and a method of creating suction [7].

It is worth being upfront about mechanism. A modern medicine overview concluded that there is no clearly identified mechanism of action for cupping, and called for more clinical research on how it works [7]. Proposed explanations, such as increased local blood flow and changes in pain signalling, remain theories rather than established facts.

What Does the Research Show?

As with many manual therapy tools, the evidence is encouraging in places but limited in quality. The findings depend on the condition, what cupping is compared against, and the time point measured.

Evidence suggesting a benefit

Chronic pain. A meta-analysis of 18 randomized trials (1,172 participants) found large short-term reductions in pain intensity with cupping compared with no treatment, and medium-sized improvements in disability compared with both no treatment and other active treatments [2].

Neck pain. A systematic review and meta-analysis of randomized trials found that cupping reduced neck pain compared with no intervention or active controls, and also when added to another treatment [1].

Musculoskeletal and sports rehabilitation. A systematic review of 22 studies rated the evidence for improving soft tissue flexibility as moderate, and the evidence for low back pain and cervical pain as low to moderate [5].

Mapping the wider literature. An evidence-mapping study of 14 meta-analyses concluded that very low to moderate quality evidence supports cupping for several pain-related conditions, including neck pain, low back pain and knee osteoarthritis [3].

Evidence suggesting limited or uncertain benefit

Sham-controlled comparisons. In the same chronic pain meta-analysis, the effect of cupping on pain was not statistically significant when compared with sham cupping [2]. This suggests that part of the observed benefit may come from non-specific effects such as touch, expectation and the treatment ritual.

No high-quality evidence. The evidence-mapping study found no high-quality evidence, using the GRADE system, demonstrating that cupping works for pain-related outcomes, and graded the methodological quality of the included reviews as mostly low or critically low [3].

Review quality and athletes. An umbrella review of systematic reviews found that most had low methodological quality. It reported that cupping performed better than passive interventions such as heat therapy, usual care, medication or no treatment, but showed similar effectiveness to acupuncture, and concluded there was not enough evidence to recommend cupping for athletes [4].

Why the evidence is inconsistent

Across these reviews, the recurring limitations are small trials, clinical heterogeneity (different cupping types, cup sizes, pressures and durations), risk of bias, and the difficulty of creating a convincing sham [2][3][4]. The sensible reading is that cupping may offer short-term benefit for some people with musculoskeletal pain, but the research does not yet allow strong claims.

Is Cupping Safe? Adverse Events and Contraindications

Cupping is generally considered relatively safe, but adverse events are not zero. A review of adverse events concluded that cupping-related events were infrequently reported but not rare, and that most were mild to moderate in severity [7]. Reported events include bruising (hematoma), pain at the application site, increased pain, tingling and dizziness [4]. In the chronic pain meta-analysis, adverse events were more frequent with cupping than with no treatment, though not significantly different from sham or other active treatment [2]. In the neck pain review, only 8 of 18 studies reported adverse events at all, and those that did described them as mostly mild and temporary [1].

An important point for training: reviews of adverse events conclude that many are avoidable when treatment is delivered by trained personnel who follow safety guidelines and infection control practices [6][7].

Commonly listed contraindications and precautions include [7]:

  • Do not apply over: veins, arteries, nerves, inflamed or damaged skin, body orifices, the eyes, lymph nodes or varicose veins.
  • Absolute contraindications include: open wounds, bone fractures and sites of deep vein thrombosis.
  • Relative contraindications include: acute infection, use of anticoagulants, severe chronic disease such as heart disease, pregnancy, menstruation, anemia, recent blood donation and a recent wet cupping session.

Good practice also means a proper intake, clear informed consent, explaining to clients that marks are expected and usually fade, and stopping if a client feels faint, or has blistering or significant pain.

What This Means for Your Practice

  • Treat it as an adjunct. Several trials tested cupping alone and as an add-on, and the add-on findings are the most practical for clinic work [1].
  • Set honest expectations. Tell clients that the research is promising but limited, and that benefits, when seen, are mostly short term [2].
  • Measure and reassess. Record pain and function before and after, and stop if the client is not benefiting.
  • Screen carefully. A thorough health history is the main protection against preventable adverse events [6][7].
  • Know your scope. Check with your regulatory college and professional liability insurer that cupping is within your scope and covered before adding it to your services.

Choosing a Cupping Therapy Course in Ontario

If you decide to add cupping to your treatments, the quality of your training matters, because safe technique, screening and infection control are what the safety literature points to [6][7]. When comparing a cupping therapy course in Ontario, it helps to ask:

  • Is it hands-on? Cup selection, pressure, and technique are practical skills best learned with supervised practice.
  • Does it cover contraindications, consent and infection control? These should be core content, not an afterthought.
  • Does it teach clinical reasoning? You should leave knowing when to use cupping, when to modify it and when to refer.
  • Does it give you a certificate you can use? Confirm that the certificate meets your regulatory college or association’s continuing education requirements.
  • Is it convenient? Practitioners across the Peel region look for cupping therapy training in Mississauga or Brampton to avoid long commutes.

Frequently Asked Questions

Does cupping therapy work for pain?

The evidence is mixed but suggests short-term benefit compared with no treatment, particularly for neck and low back pain. However, it was not significantly better than sham cupping in a major meta-analysis, and no high-quality evidence has been found [2][3].

Is cupping therapy safe?

It is relatively safe when performed by trained practitioners who screen clients properly. Adverse events such as bruising and pain at the site are mostly mild to moderate, but they are not rare [4][7].

Do I need certification to learn cupping?

Requirements depend on your profession and regulatory body. Regardless, formal training in technique, contraindications and infection control is strongly supported by the safety literature [6][7]. Check your college and insurer.

Is cupping the same as Gua Sha?

No. Cupping uses suction, while Gua Sha uses a tool to scrape or glide over the skin. Read our guide to Gua Sha vs. IASTM for how tool-based soft tissue techniques compare.

Conclusion

Cupping is a popular, generally well-tolerated technique that may give some clients short-term relief from musculoskeletal pain, particularly as an add-on to other care. The research does not yet show that it outperforms sham treatment, and the quality of the evidence is limited. For practitioners, the value lies in careful screening, skilled and hygienic technique, honest communication and regular reassessment.

If you would like to learn cupping in a supervised, hands-on setting, explore The Canadian Health Academy’s Cupping Therapy course at our Mississauga location, or visit our Registration page for upcoming dates. Practitioners in Brampton can also see our Continuing Education Brampton page for healthcare continuing education options. As a health academy in Ontario, we offer healthcare training and therapy courses for practitioners who want to expand their skills, and you can browse all of our courses here.

This article is for educational purposes for healthcare and wellness professionals and does not replace individual clinical assessment. Check your regulatory college and insurer regarding scope of practice.

References

  1. Kim S, Lee SH, Kim MR, et al. Is cupping therapy effective in patients with neck pain? A systematic review and meta-analysis. BMJ Open. 2018;8(11):e021070. doi:10.1136/bmjopen-2017-021070
  2. Cramer H, Klose P, Teut M, et al. Cupping for patients with chronic pain: a systematic review and meta-analysis. Journal of Pain. 2020;21(9-10):943-956. doi:10.1016/j.jpain.2020.01.002
  3. Wang L, Cai Z, Li X, Zhu A. Efficacy of cupping therapy on pain outcomes: an evidence-mapping study. Frontiers in Neurology. 2023;14:1266712. doi:10.3389/fneur.2023.1266712
  4. Elmeligie MM, Yehia AH, Hamada Mohamed M, et al. Effectiveness of cupping therapy for musculoskeletal pain: an umbrella review. Human Movement
  5. Mohamed AA, Zhang X, Jan YK. Evidence-based and adverse-effects analyses of cupping therapy in musculoskeletal and sports rehabilitation: a systematic and evidence-based review. Journal of Back and Musculoskeletal Rehabilitation. 2023;36(1):3-19. doi:10.3233/BMR-210242
  6. Kim TH, Kim KH, Choi JY, Lee MS. Adverse events related to cupping therapy in studies conducted in Korea: a systematic review. European Journal of Integrative Medicine. 2014;6(4):434-440.
  7. Cupping Therapy: An Overview from a Modern Medicine Perspective. Journal of Acupuncture and Meridian Studies. 2018. iam.biomedcentral.com
Read More
Gua Sha vs IASTM comparison chart showing differences in origin, approach, tools and typical goals

Gua Sha vs. IASTM: What’s the Difference, and Which Should You Learn?

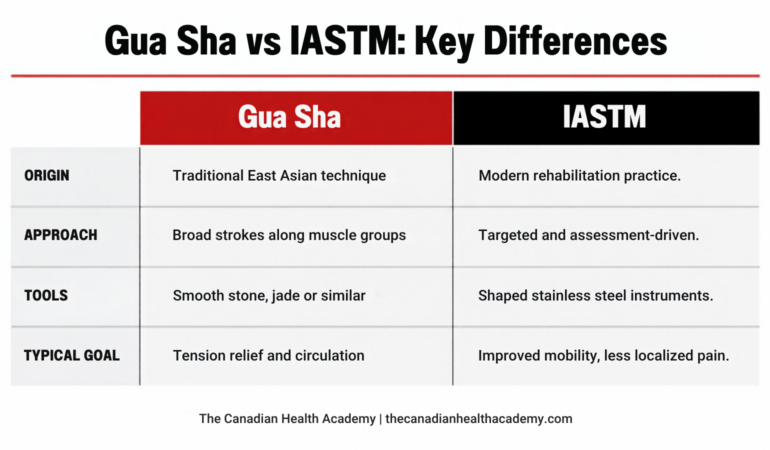
Clients are asking about both, and the two are often lumped together. Gua Sha vs IASTM is one of the most common questions practitioners have when deciding which hands-on tool technique to add to their practice. Both use a smooth-edged tool on the skin to influence soft tissue, but they come from different traditions and are used for different reasons.

What Is Gua Sha?

Gua Sha is a traditional East Asian technique. The practitioner applies oil, then strokes the skin with a smooth tool, often in long, repeated strokes. It can leave temporary redness or small red marks called “sha,” which is part of the traditional approach. Gua Sha is commonly used for muscle tension, circulation and general wellness work.

What Is IASTM?

Instrument-Assisted Soft Tissue Mobilization (IASTM) is a modern, clinically oriented method. Practitioners use specially shaped tools, often stainless steel, to assess and treat soft tissue restrictions. It is popular in rehabilitation and sports settings, where the goal is usually to improve mobility and reduce pain around a specific area.

Gua Sha vs IASTM: The Key Differences

  Gua Sha IASTM
Origin Traditional East Asian technique Modern rehabilitation practice
Approach Broad strokes along muscle groups Targeted and assessment-driven
Tools Smooth stone, jade or similar materials Shaped stainless steel instruments
Typical goal Tension relief and circulation Improved mobility and less localized pain

Research on both techniques is still developing and results are mixed, so practitioners should be honest with clients about expected outcomes.

Which Should You Learn: Gua Sha or IASTM?

It depends on your clientele. If you work in wellness or relaxation-focused massage, Gua Sha training is a natural fit. If you treat sports injuries or movement restrictions, IASTM certification may serve you better. Many practitioners find the two complement each other, and learning the foundations of both means you can choose the right tool for each client.

A Note on Scope of Practice

Before adding either technique, check with your regulatory college (for example, the College of Massage Therapists of Ontario for Registered Massage Therapists) and your insurer to confirm it falls within your scope of practice.

Train With The Canadian Health Academy

Our Gua Sha & IASTM course teaches both techniques in a hands-on setting for massage therapists, healthcare professionals and wellness practitioners. Explore all of our CEU-accredited training on our courses page.

Read More

Your Clients Have Seen the Brazilian Lymphatic Drainage Videos. Can You Deliver It?

Graphic announcing a live session on Manual and Brazilian Lymphatic Drainage on Thursday, October 8

Scroll through social media for five minutes and you’ll see it: fast, sculpting strokes, dramatic before-and-after clips, and millions of views. Brazilian Lymphatic Drainage has gone from a niche technique to one of the most requested treatments in wellness. Now clients are walking into clinics and spas asking for it by name.

Here’s what most of those videos don’t tell you. Behind the trend is a clinical method that has been practised and refined for almost a century. Manual Lymphatic Drainage (MLD) was developed in the 1930s. It is the gentle, rhythmic, evidence-informed technique used alongside healthcare teams around the world.

The two methods sound alike, but they are not the same treatment. Practitioners who understand the difference, and can offer both responsibly, are the ones clients book and rebook.

On Thursday, October 8, The Canadian Health Academy is hosting a live session that breaks it all down.

What We’ll Cover

  • The lymphatic system, made practical. You’ll get a clear, hands-on understanding of how lymph moves through the body. You’ll also learn why direction, pressure and rhythm matter so much in any drainage technique.
  • Manual Lymphatic Drainage (MLD). We’ll cover the principles behind the classic clinical approach: light pressure, slow repetitive strokes and a precise sequence. We’ll also look at where MLD fits in a professional practice.
  • Brazilian Lymphatic Drainage. You’ll see what makes this faster, more vigorous, aesthetics-focused method different. We’ll explain why it has exploded in popularity and what clients usually expect when they book it.
  • Side-by-side comparison. We’ll compare pressure, pace, goals and session flow, and which client suits which approach. That way you can answer the question “which one do I need?” with confidence.
  • Safety and contraindications. You’ll learn when lymphatic work is not appropriate, when to refer out, and how to set honest expectations. That means no overpromising, and no “detox” or weight-loss claims.
  • Building it into your business. We’ll go over how certified lymphatic drainage training can expand your service menu, support CEU requirements and set you apart in a crowded market.
  • Live Q&A. Bring your questions about technique, clients and certification pathways.

Who This Session Is For

This session is for Registered Massage Therapists, estheticians, spa and wellness practitioners, and healthcare professionals looking to grow their skills. It’s also for anyone who keeps getting asked about lymphatic drainage and wants to answer like an expert.

Session Details

Date: Thursday, October 8, 2026
Time: 10:30 am 5:30 pm
Format: in person at 1425 Dundas St E., Mississauga.
Cost:
– MLD Level 1 – $500
– MLD Level 2 – $500
– Brazialin MLD – $500
– All 3 courses – $800 – BEST VALUE

Reserve Your Spot

Spaces are limited so everyone can get their questions answered. If clients are already asking you about lymphatic drainage, this is the session that gets you ready.

Questions? Call +1.647.239.9952 or email info@thecanadianhealthacademy.com.

Want to go further? Explore our full Manual Lymphatic Drainage certification course in Mississauga and Brampton.

Read More

What Is K-Taping and How Does It Help Relieve Pain? An Evidence-Based Guide for Practitioners

Brightly coloured elastic tape on athletes’ shoulders, knees and backs is now a familiar sight in clinics and on the sports field. Kinesiology taping, often called K-Taping, is one of the most widely used adjunct tools in rehabilitation, and patients frequently ask about it by name. For physiotherapists, massage therapists, kinesiologists and other healthcare practitioners, the key questions are practical: what exactly is it, how is it thought to relieve pain, and what does the research really show? This article answers those questions using the published evidence.

What Is K-Taping?

Kinesiology taping uses a thin, elastic, adhesive tape applied directly to the skin. The method was developed in the 1970s by Dr Kenzo Kase, a Japanese chiropractor, originally to aid muscle movement and support athletic performance [1][2]. The tape was first exhibited internationally at the 1988 Seoul Olympics and became widely popular after the 2008 Beijing Olympics, when high-profile athletes were seen wearing it [2].

Unlike rigid athletic tape, which restricts joint movement, kinesiology tape is designed to stretch and move with the body. Its key properties include [3]:

  • It can stretch to roughly 120–140% of its original length.
  • It uses a heat-activated adhesive and is latex-free.
  • It can be worn for several days, including in water.

Applications vary by tape cut (I, Y, X, fan and others), the amount of stretch applied, the direction of application and the position of the patient. Practitioners choose these according to their assessment of the tissue being targeted [3].

How Is K-Taping Thought to Relieve Pain?

Several mechanisms have been proposed. It is important to note that these are theories, and not all have been confirmed by research.

  • Neurophysiological (sensory) effects: The tape creates pressure and stretch on the skin, which may stimulate cutaneous mechanoreceptors. This sensory input is thought to interact with the central nervous system and modulate pain responses [3].
  • Skin lifting and circulation: Applying the tape is suggested to lift the skin and increase the space beneath it. Proponents propose that this improves blood flow and lymphatic drainage, which may help reduce swelling and pain [1].
  • Muscle activation: The tape is also suggested to help activate muscles, which may contribute to pain reduction and strength [1].

One well-designed trial directly tested the “skin lifting” theory. In 148 people with chronic non-specific low back pain, tape applied with stretch to create skin convolutions was no more effective than the same tape applied without tension. The authors concluded that their results challenge the proposed mechanism of action [4].

What Does the Research Show?

The evidence on K-Taping for pain is mixed. Findings depend heavily on the condition, the comparison group and the time point measured.

Evidence suggesting a benefit

Compared with minimal or no intervention. A meta-analysis of 17 trials in people with musculoskeletal pain lasting more than four weeks found that kinesiology taping gave better pain relief than minimal intervention. Disability scores, however, were not significantly different [5].

Myofascial pain syndrome. A 2025 meta-analysis of 15 randomized controlled trials found that kinesiology taping significantly reduced pain intensity compared with control groups (no intervention, placebo or sham taping). The effect was seen immediately after application, within the first week and at two to three weeks, but it diminished by four to six weeks [1].

As an adjunct to other treatment. A systematic review and meta-analysis including 36 studies found improvements in both pain and disability across body regions. The authors concluded that their findings support kinesiology taping as an adjuvant to other treatments for musculoskeletal disorders [6].

Evidence suggesting limited or no benefit

Compared with sham taping and other treatments. A systematic review of 12 randomized controlled trials (495 patients) covering shoulder, knee, back and neck pain, plantar fasciitis and mixed conditions found that kinesiology taping was no better than sham taping or active comparison treatments. Where it did perform better, the effect sizes were small and probably not clinically significant, or the trials were of low quality [7][8].

Chronic musculoskeletal pain. The same meta-analysis that found benefit over minimal intervention also concluded that existing evidence does not establish that kinesiology taping is superior to other treatment approaches for reducing pain and disability [5].

Shoulder disorders. A 2020 meta-analysis found that kinesiology taping did not produce better results for pain than sham taping, exercise or passive treatments, and concluded there is no firm evidence of benefit for shoulder disorders [9].

Musculoskeletal injury. An earlier meta-analysis of 13 studies concluded that kinesiology tape may have limited potential to reduce pain in people with musculoskeletal injuries, and that depending on the condition, any reduction may not be clinically meaningful [10].

Why the evidence is inconsistent

Several factors make the research difficult to interpret. Studies use different tape brands with different material properties, inconsistent application protocols and practitioners with varying levels of taping training. Some research is also conducted on healthy participants rather than people with injuries [3]. These limitations mean that neither strong claims of effectiveness nor outright dismissal are fully supported by the current literature.

What This Means for Your Practice

Taken together, the evidence supports a measured, patient-centred approach:

  • Use it as an adjunct, not a stand-alone treatment. The most supportive evidence positions kinesiology taping alongside other treatments, such as exercise and manual therapy [6].
  • Expect short-term effects. Pain benefits, where seen, are most consistent in the immediate and short term [1].
  • Set honest expectations. Tell patients that the research is mixed and that the tape is one part of their overall plan.
  • Reassess and discontinue if there is no benefit. Measure pain and function before and after application, and stop taping if it isn’t helping.
  • Get trained. Application technique, tension and direction are central to the method, and trained application is part of good practice [3].

Contraindications and Precautions

Commonly listed general contraindications for kinesiology taping include [3]:

  • Malignancy
  • Infection or cellulitis
  • Open wounds
  • Deep vein thrombosis (DVT)
  • Previous allergic reaction to the tape

General precautions include diabetes, congestive heart failure, kidney disease or dialysis, organ transplants and pregnancy [3].

Good practice also includes applying tape to clean, dry skin free of oils and lotions. Tell patients to remove the tape if they notice itching, burning or increased pain, and teach them how to remove it safely [3]. Skin irritation and allergic reaction are recognized downsides of taping [3].

Frequently Asked Questions

Does K-Taping work for pain?

The evidence is mixed. Kinesiology taping has outperformed minimal intervention for chronic musculoskeletal pain [5] and reduced pain in the short term in myofascial pain syndrome [1]. However, several reviews found it no better than sham taping or other treatments [7][9].

How long does kinesiology tape stay on?

It is designed to be worn for several days, including during showering and swimming [2][3].

Is K-Taping the same as athletic taping?

No. Traditional athletic tape is rigid and restricts movement, while kinesiology tape is elastic and allows movement.

Conclusion

K-Taping is a popular, generally well-tolerated tool that may provide short-term pain relief for some patients, particularly when combined with active treatment. The research does not show that it outperforms sham taping or other interventions across the board. The value for practitioners lies in skilled application, careful patient selection, honest communication and regular reassessment.

If you want to learn kinesiology taping application techniques in a supervised, hands-on setting, explore The Canadian Health Academy’s K-Taping course or visit our Registration page for upcoming dates.

This article is for educational purposes for healthcare and wellness professionals and does not replace individual clinical assessment.

References

  1. Kandeel M, et al. A Systematic Review and Meta-Analysis of the Efficacy of Kinesio Taping for Pain Management and Pressure Pain Threshold in Myofascial Pain Syndrome. Pain Research and Management. 2025;2025:8881632. doi:10.1155/prm/8881632
  2. Does kinesio tape alter muscle strength in athletes? Systematic review and meta-analysis. Journal of Bodywork and Movement Therapies. 2023. ScienceDirect
  3. Physiopedia. Kinesio Taping. physio-pedia.com/Kinesio_Taping
  4. Parreira PCS, Costa LCM, Takahashi R, et al. Kinesio Taping to generate skin convolutions is not better than sham taping for people with chronic non-specific low back pain: a randomised trial. Journal of Physiotherapy. 2014;60:90–96. doi:10.1016/j.jphys.2014.05.003
  5. Lim EC, Tay MG. Kinesio taping in musculoskeletal pain and disability that lasts for more than 4 weeks: is it time to peel off the tape and throw it out with the sweat? A systematic review with meta-analysis. British Journal of Sports Medicine. 2015. PubMed 25595290
  6. Efficacy of Kinesio Taping Compared to Other Treatment Modalities in Musculoskeletal Disorders: A Systematic Review and Meta-Analysis. Research in Sports Medicine. 31(4). doi:10.1080/15438627.2021.1989432
  7. Parreira PdCS, Costa LdCM, Hespanhol Junior LC, Lopes AD, Costa LOP. Current evidence does not support the use of Kinesio Taping in clinical practice: a systematic review. Journal of Physiotherapy. 2014;60(1):31–39. doi:10.1016/j.jphys.2013.12.008
  8. International Association for the Study of Pain (IASP). Kinesio Taping looks so cool, but is it effective? iasp-pain.org
  9. Celik D, Karaborklu Argut S, Coban O, Eren I. The clinical efficacy of kinesio taping in shoulder disorders: a systematic review and meta analysis. Clinical Rehabilitation. 2020. doi:10.1177/0269215520917747
  10. Montalvo AM, Le Cara E, Myer GD. Effect of Kinesiology Taping on Pain in Individuals With Musculoskeletal Injuries: Systematic Review and Meta-Analysis. The Physician and Sportsmedicine. 2014;42(2). doi:10.3810/psm.2014.05.2057
Read More

Manual Lymphatic Drainage After Liposuction: What the Evidence Says for Practitioners

Liposuction remains one of the most requested cosmetic procedures, and many clients now arrive at the treatment room within weeks of surgery asking for “lymphatic massage.” For physiotherapists, massage therapists and holistic practitioners, this is both an opportunity and a responsibility. Manual Lymphatic Drainage (MLD) has a sound physiological rationale in the post-liposuction period, but the research specific to liposuction is still small. This article summarizes what the published evidence actually shows, where it falls short, and how to apply MLD safely and professionally with post-surgical clients.

Why Swelling Follows Liposuction

Under normal conditions, fluid filters out of the blood capillaries into the tissue spaces and the surplus is collected by the lymphatic vessels and returned to the venous circulation. A 2023 review in Aesthetic Surgery Journal Open Forum notes that this equilibrium is routinely disrupted by surgical and cosmetic procedures, including liposuction and body contouring [1].

The same review reports that postoperative swelling after aesthetic procedures, especially liposuction, can take between three and six months to resolve. The authors also describe how fluid accumulation after liposuction can produce hardened lumps and bumps in the skin, similar in appearance to the tissue changes of chronic lymphedema [1].

There is one important distinction. The authors point out that people having elective cosmetic procedures generally have a healthy, intact lymphatic system, unlike patients with lymphedema [1]. In other words, post-liposuction swelling is usually a temporary overload of a normal system rather than a failure of the system itself. That is the reason MLD is considered a supportive therapy in this setting rather than a treatment for disease.

What the Research Shows

Practitioners should know the studies behind the claims their clients read online. Here is a summary of the most relevant published work.

1. MLD after abdominoplasty with liposuction (Maningas et al., 2020)

This prospective comparative study followed 20 women after abdominoplasty with core liposuction. All participants wore a standard compression garment for eight weeks. Starting six weeks after surgery, the treatment group received MLD from a certified lymphedema specialist twice a week for three weeks (six visits) [2].

Waist circumference fell by an average of 9.8 cm between weeks six and eight in the MLD group, compared with 6.6 cm in the compression-only group. However, the difference between groups was not statistically significant (P = .11). The authors concluded that MLD reduced edema more than compression garments alone, but not by a statistically significant amount [2]. The small sample and the fact that groups were assigned by clinic location rather than randomization limit how far this can be generalized.

2. MLD combined with therapeutic ultrasound (Masson et al., 2014)

This Brazilian clinical trial included 18 women aged 18 to 60 in the late postoperative period after liposuction or lipoabdominoplasty of the abdomen, flanks and lower trunk, all of whom had tissue fibrosis in those regions. Participants received twelve sessions of therapeutic ultrasound followed by MLD [3].

The researchers reported statistically significant reductions in pain, swelling and tissue fibrosis in both the liposuction and lipoabdominoplasty groups [3]. Because MLD was always combined with ultrasound and there was no untreated control group, the study cannot show how much of the benefit came from MLD itself. The authors also noted that most participants were wearing compression during the study, which may have influenced fibrosis resolution [3].

3. MLD versus shockwave therapy for cellulite after liposuction (Allam et al., 2021)

In this randomized trial, 30 women with grade 3 cellulite after liposuction received either extracorporeal shockwave therapy (ESWT) or MLD twice weekly for four weeks, with both groups also using topical retinol. Skinfold thickness decreased by 15.38% in the MLD group and by 24.4% in the ESWT group, and ESWT produced significantly greater improvement in cellulite grade [4].

The practical takeaway is that MLD was associated with improvement. For cellulite and subcutaneous thickness specifically, however, it was outperformed by another modality in this study.

4. The broader post-surgical picture

Outside cosmetic surgery, the evidence for MLD after surgery is mixed. A 2026 systematic review of MLD after total knee arthroplasty (eight RCTs, 463 participants) found that edema data were too limited for reliable pooling. MLD did not produce consistent improvements in range of motion or pain, although two studies reported modest, short-lived benefits in the first postoperative days [5]. This is a useful reminder that MLD’s benefits after surgery should be presented to clients honestly, not oversold.

Potential Benefits for the Post-Liposuction Client

Taken together, the available literature supports the following possible benefits of MLD after liposuction, usually alongside compression:

  • Support for edema resolution: MLD may assist the lymphatic system in reabsorbing the fluid load created by surgery [1], with a favourable but not statistically significant trend in the only controlled liposuction study [2].
  • Reduction of fibrosis and firmness: Reductions in tissue fibrosis were reported when MLD was combined with therapeutic ultrasound [3].
  • Pain relief: Pain decreased significantly in the combined MLD and ultrasound protocol [3].
  • Client comfort and engagement in recovery: A structured, hands-on recovery plan gives clients a professional point of contact during a recovery period that can last several months [1].

What the evidence does not yet support is the idea that MLD is essential after every liposuction, that it guarantees a better aesthetic result, or that it can replace the surgeon’s instructions on compression and activity.

Safety First: Contraindications and Red Flags

The American Society of Plastic Surgeons lists potential liposuction risks that include deep vein thrombosis, cardiac and pulmonary complications, infection, fluid accumulation, poor wound healing, persistent swelling and contour irregularities [6]. Several of these can resemble “normal swelling” to an untrained eye.

Before treating, practitioners should:

  • Obtain surgeon clearance and follow the surgeon’s post-operative protocol, including when manual therapy may begin and which areas to avoid.
  • Screen for standard MLD contraindications taught in recognized training, such as active infection or fever, suspected or untreated deep vein thrombosis, decompensated heart failure and significant renal impairment.
  • Avoid open incisions and unhealed tissue, and respect any drains or dressings in place.

Refer the client back to their surgeon, or to emergency care where appropriate, if you notice:

  • Increasing redness, heat, discharge or fever (possible infection)
  • One-sided calf pain, warmth or swelling (possible DVT)
  • Shortness of breath or chest pain, which requires emergency care
  • A soft, rapidly enlarging or fluctuant swelling (possible fluid collection)
  • Wound separation or skin discolouration that worsens between visits

Practical Considerations for Your Practice

Timing and frequency. There is no standardized protocol. In the published studies, MLD began at six weeks after surgery [2] or in the late postoperative period [3], and was delivered twice weekly for three to four weeks [2][4] or over twelve sessions [3]. Always defer to the operating surgeon on start dates.

Work with compression, not against it. Compression garments were part of the standard care in every study reviewed here [2][3]. Encourage clients to follow their surgeon’s garment instructions and to put the garment back on after sessions if instructed.

Measure outcomes. Simple, repeatable measures such as circumference at fixed landmarks (as used by Maningas et al. [2]), pain scores and client-reported firmness help you track progress and communicate professionally with the surgical team.

Know your scope. MLD is a specialized technique. Physiotherapists, registered massage therapists and holistic practitioners should hold proper MLD training and practise within their regulatory scope and insurance coverage.

Frequently Asked Questions

Is Manual Lymphatic Drainage necessary after liposuction?

Current evidence does not show it is essential for every patient. Small studies suggest it may support swelling, fibrosis and pain reduction, usually alongside compression [2][3].

When can MLD start after liposuction?

Only after the operating surgeon gives clearance. Published studies started at different points, including six weeks post-surgery [2].

Is MLD the same as deep tissue massage?

No. MLD is a gentle, specialized technique aimed at stimulating lymphatic flow, and it is a component of complete decongestive therapy used in lymphedema care [1].

Can MLD fix lumps and firmness after liposuction?

One study reported reduced fibrosis when MLD was combined with therapeutic ultrasound [3], but no study has isolated MLD alone for this outcome.

Conclusion

Manual Lymphatic Drainage has a clear physiological rationale after liposuction and encouraging, though limited, supporting evidence. For practitioners, the value lies in applying it skilfully, safely and honestly: with surgeon collaboration, careful screening and realistic expectations. As demand for post-surgical care grows, well-trained practitioners are best placed to meet it.

If you want to build or formalize your skills in this area, read our guide on Online vs In Person MLD Certification and explore The Canadian Health Academy’s Manual Lymphatic Drainage training through our Registration page.

This article is for educational purposes for health and wellness professionals and does not replace medical advice or the instructions of the operating surgeon.

References

  1. Marxen T, Shauly O, Goel P, Tsan T, Faria R, Gould DJ. The Utility of Lymphatic Massage in Cosmetic Procedures. Aesthetic Surgery Journal Open Forum. 2023;5:ojad023. doi:10.1093/asjof/ojad023
  2. Maningas T, Sturm L, Mangler A, Pazdernik VK. Manual Lymphatic Drainage in Postoperative Abdominoplasty With Core Liposuction Patients. The American Journal of Cosmetic Surgery. 2020;37(1):45-49. doi:10.1177/0748806819874941
  3. Masson IF, de Oliveira BD, Machado AF, Farcic TS, Júnior IE, Baldan CS. Manual lymphatic drainage and therapeutic ultrasound in liposuction and lipoabdominoplasty post-operative period. Indian Journal of Plastic Surgery. 2014;47(1):70-76. doi:10.4103/0970-0358.129627
  4. Allam NM, Elshorbagy RT, Eid MM, Abdelbasset WK, Elkholi SM, Eladl HM. Comparison of Extracorporeal Shock Wave Therapy versus Manual Lymphatic Drainage on Cellulite after Liposuction: A Randomized Clinical Trial. Evidence-Based Complementary and Alternative Medicine. 2021;2021:9956879. doi:10.1155/2021/9956879
  5. Papi D, Carulli C, Lorenzoni N, Montigiani G. Effectiveness of Manual Lymphatic Drainage After Total Knee Arthroplasty: A Systematic Review. Journal of Clinical Medicine. 2026. doi:10.3390/jcm15145575
  6. American Society of Plastic Surgeons. Liposuction: Risks and Safety. plasticsurgery.org
Read More

Online vs In Person MLD Certification: Which One Is Right for You? 

As Manual Lymphatic Drainage (MLD) continues to grow in popularity across wellness, rehabilitation, post-operative care, aesthetic treatments, and holistic therapies, more healthcare practitioners, yoga instructors, and wellness professionals are asking an important question:

Should I take my MLD certification online or in person?

The answer depends on your goals, learning style, professional background, and the type of clients you plan to treat.

At The Canadian Health Academy, we believe practitioners deserve an educational experience that builds both confidence and competence. Before investing your time and money, it’s important to understand the strengths and limitations of each training format.


What Is Manual Lymphatic Drainage (MLD)?

Manual Lymphatic Drainage is a gentle, rhythmic therapy designed to stimulate lymphatic flow, reduce swelling, improve circulation, support detoxification, and enhance the body’s natural healing processes.

MLD is commonly used for:

  • Post-operative recovery
  • Wellness and spa therapies
  • Chronic inflammation support
  • Edema and fluid retention
  • Sports recovery
  • Stress reduction and nervous system regulation
  • Oncology and lymphedema support
  • Cosmetic and facial treatments

Because MLD is a highly tactile modality, the quality of training plays a critical role in treatment outcomes.


The Rise of Online MLD Certification Programs

Online education has transformed healthcare learning, making professional development more accessible than ever.

Advantages of Online Learning

Online MLD programs often offer:

  • Flexible scheduling
  • Lower travel and accommodation costs
  • Learning from the comfort of home
  • Recorded modules for repeated review
  • Accessibility for busy professionals

For theory-based topics such as:

  • Lymphatic anatomy
  • Physiology
  • Contraindications
  • Treatment indications
  • Clinical research
  • Documentation and business practices

online education can be highly effective.

Many programs also include:

  • Video demonstrations
  • Live webinars
  • Virtual mentorship
  • Case-study reviews
  • Continuing Education Unit (CEU) credits

Online learning can be especially beneficial for practitioners who already possess strong hands-on therapy skills and are seeking to expand their knowledge.


The Biggest Limitation of Online MLD Training

While online education is excellent for theoretical learning, MLD is ultimately a hands-on sensory skill.

Critical elements such as:

  • Pressure control
  • Direction of movement
  • Treatment rhythm
  • Skin stretch techniques
  • Hand positioning
  • Treatment sequencing
  • Tissue feedback interpretation

are difficult to fully master through video instruction alone.

Why Hands-On Practice Matters

In MLD, subtle differences can significantly impact treatment effectiveness:

  • Excessive pressure can compress lymphatic vessels
  • Incorrect sequencing may reduce therapeutic outcomes
  • Poor body mechanics can lead to practitioner fatigue
  • Inconsistent technique can produce inconsistent clinical results

This is where supervised, in-person training becomes invaluable.


Benefits of In-Person MLD Certification

In-person training provides opportunities that simply cannot be replicated online.

Students benefit from:

  • Feeling the correct pressure and treatment rhythm
  • Real-time instructor feedback and corrections
  • Practicing on different body types and conditions
  • Refining hands-on treatment techniques
  • Learning proper ergonomic body mechanics
  • Developing effective time-management skills
  • Improving client communication
  • Building confidence through supervised practice
  • Receiving immediate answers to questions
  • Learning business, sales, and marketing strategies

For manual therapy disciplines, practical experience directly contributes to improved treatment outcomes and practitioner confidence.


Who Benefits Most from Online MLD Training?

Online certification may be ideal for:

  • Experienced massage therapists
  • Healthcare professionals seeking refresher education
  • Practitioners with previous MLD experience
  • Students wanting to learn theory before practical training
  • Busy professionals requiring schedule flexibility
  • Practitioners in remote or underserved locations

Online learning is also excellent for:

  • Continuing education
  • Advanced theoretical concepts
  • Specialty applications
  • Review modules
  • Ongoing mentorship and professional development

However, fully online programs may not provide sufficient tactile training for individuals learning MLD for the first time.


Who Should Choose In-Person Training?

In-person MLD certification is often the best choice for:

  • Beginners
  • New graduates
  • Hands-on learners
  • Practitioners seeking immediate confidence
  • Therapists planning to specialize in lymphatic therapy
  • Professionals treating post-operative clients
  • Practitioners working with complex swelling or edema conditions

If your goal is to safely and confidently integrate MLD into clinical practice as quickly as possible, supervised practical training is typically the strongest pathway.


The Best of Both Worlds: Hybrid MLD Programs

Many leading educational institutions now offer hybrid MLD certification programs, combining the advantages of both online and in-person learning.

A hybrid model typically includes:

Online Components

  • Anatomy and physiology
  • Lymphatic system theory
  • Treatment indications and contraindications
  • Pre-course study materials
  • Video demonstrations

In-Person Components

  • Practical workshops
  • Supervised treatment practice
  • Instructor assessment and feedback
  • Hands-on skill development
  • Clinical application training

Benefits of Hybrid Learning

Students can:

  1. Learn theory at their own pace
  2. Attend focused hands-on intensives
  3. Practice under expert supervision
  4. Receive personalized mentorship and feedback

Hybrid education is becoming increasingly popular because it balances convenience with clinical competency.


Why Choose The Canadian Health Academy for MLD Certification?

Before enrolling in any MLD program, consider the following questions:

1. Is the Training Truly Hands-On?

Students should receive direct assessment of:

  • Pressure
  • Sequencing
  • Technique
  • Body mechanics

2. Are the Instructors Experienced Clinicians?

Learning from practitioners with real-world clinical experience provides valuable practical insights beyond textbook knowledge.

3. How Much Training Is Included?

Our MLD Level 1 and Level 2 programs provide a combined 32 hours of comprehensive instruction.

4. Is Mentorship Available After Graduation?

Ongoing support often transforms knowledge into confidence and helps graduates successfully implement MLD in practice.

5. Is the Certification Accredited and Recognized?

Choose a program that offers third-party accreditation and professional recognition within the healthcare and wellness communities.

6. Does the Program Align With Your Career Goals?

Whether your focus is:

  • Spa and wellness treatments
  • Post-operative recovery
  • Clinical edema management
  • Oncology support

your education should prepare you for your desired specialty.


Our Perspective at The Canadian Health Academy

At The Canadian Health Academy, we believe effective MLD education should combine:

  • Strong scientific foundations
  • Practical hands-on training
  • Clinical reasoning
  • Safety-focused instruction
  • Real-world application
  • Business growth strategies
  • Marketing and client acquisition skills

While online education is a powerful learning tool, hands-on mentorship remains one of the most important components of developing safe, effective, and confident manual therapy practitioners.

The best educational experience doesn’t simply provide information—it develops clinical confidence.


Final Thoughts

Online MLD certification offers flexibility, convenience, and accessibility.

In-person training provides tactile experience, direct mentorship, and clinical confidence.

Neither format is inherently better. The right choice depends on:

  • Your experience level
  • Preferred learning style
  • Professional goals
  • Budget
  • Time availability
  • Desired depth of clinical training

For many practitioners, a hybrid learning approach offers the ideal balance between flexibility and hands-on mastery.

As the field of lymphatic therapy continues to evolve, one principle remains unchanged:

The quality of your training directly influences the quality of care you provide to your clients.

Ready to begin your MLD journey? Explore certification options that combine evidence-based education, hands-on training, and ongoing mentorship to help you succeed in practice.

Read More
Book Your Appointment